- Minimally invasive
- Motion preserving
- Open procedures

 Pinched nerve
 Spinal cord compression
Anterior Cervical Discectomy And Fusion. Using an approach from the front of the neck, we remove the herniated disc that is compressing your nerve or spinal cord. A spacer is then placed in between the bones where the disc used to be. Over time the two bones fuse together. Additional details about ACDF, anterior cervical discectomy and fusion
Pinched nerve
Working from the back of the neck through a small tube, we widen the opening where the nerve leaves the spine to take the pressure off it. The disc is left in place and nothing is fused. Additional details about Cervical foraminotomy
Pinched nerve
Spinal cord compression
Using the same approach from the front of the neck, we remove the damaged disc and take the pressure off the nerve or spinal cord. Instead of fusing the bones, we put in an artificial disc that lets the neck keep moving at that level. Not everyone is a candidate, and your imaging decides. Additional details about Cervical disc replacement
↑ Treated by the three above
Cervical radiculopathy
A disc or bone spur is pressing on a nerve where it leaves your neck. You may feel pain, tingling or weakness running down into your shoulder, arm or hand. Most cases get better without surgery.
Cervical stenosis and myelopathy
The spinal canal in your neck has narrowed and is squeezing your spinal cord. You may notice clumsy hands, trouble with buttons or handwriting, or poor balance more than neck pain. The spinal cord recovers less well than a nerve, so timing matters.
Spinal cord compression
Working from the back of the neck, we hinge open the bony roof of the spinal canal to give the spinal cord more room across several levels. This procedure preserves the motion of the spine. It can be used in select cases. Additional details about Cervical laminoplasty
Spinal cord compression
Working from the back of the neck, we take the pressure off the spinal cord and hold several levels still with screws and rods. Over time the bones fuse together. We use it when the problem runs along much of the neck or the alignment needs correcting. Additional details about Posterior cervical fusion
 Pinched nerve
 Spinal stenosis
Through a small tube in the lower back, we remove the piece of disc or bone that is pressing on your nerve. The muscle is moved aside without being cut, and nothing is fused. This is the most common spine operation. Additional details about Microdiscectomy and laminectomy
Pinched nerve
Spinal stenosis
Using an approach from the front of the abdomen, we remove the worn disc and put in an artificial one that keeps the level moving. Very few people are candidates, and your imaging decides. Additional details about Lumbar disc replacement
Pinched nerve
Spinal stenosis
 Instability
Minimally Invasive Transforaminal Lumbar Interbody Fusion. Through small incisions in the back, we take the pressure off the nerve and remove the worn disc. A spacer goes in where the disc used to be, and screws and rods hold the level still while the two bones fuse together. Additional details about MIS TLIF
Lumbar radiculopathy
A disc or bone spur is pressing on a nerve root in your lower back. You may feel pain, numbness or weakness running down your leg, often called sciatica. Most cases get better without surgery.
Legs tire and ache on walking
The spinal canal in your lower back has narrowed and is crowding the nerves inside it. Your legs tire and ache after walking a short way, and feel better when you sit down or lean forward.
Degenerative spondylolisthesis
One of the bones in your lower back has slipped forward on the one below. When we take the pressure off your nerves at that level, we usually fuse it too, because removing bone from an unstable level can make it worse.
Spinal stenosis
Working from the back, we remove the bone and thickened ligament that are crowding the nerves across three or more levels of the lower back. If the spine is stable, no fusion is needed. Additional details about Multilevel laminectomy
Pinched nerve
Spinal stenosis
Instability
Working from the back, we correct the alignment of the spine and fuse several levels together with screws and rods. We use it for deformity, for revising earlier surgery, and when the spine has lost its balance over the pelvis. We plan it on standing X-rays of the whole spine. Additional details about Multilevel lumbar fusion
Pinched nerve
Spinal stenosis
Instability
Through a small incision in your side, we reach the spine and place a large spacer where the disc used to be. This restores the height of the disc and gives the nerves more room without entering the spinal canal. It cannot reach the lowest level, L5–S1. Additional details about Lateral lumbar fusion (XLIF / DLIF)
Pinched nerve
Spinal stenosis
Instability
Using an approach from the front of the abdomen, we remove the worn disc and place a large spacer between the bones, without touching the back muscles. Over time the two bones fuse together. It is the usual choice at L5–S1. Additional details about ALIF, anterior lumbar fusion
The two common reasons for fusion are an unstable spine, where the bones are sliding back and forth, or neuroforaminal stenosis, a type of nerve compression that occurs when nerves become entrapped as they exit the spine through a tunnel called the neural foramen. This is usually due to severe disc collapse.
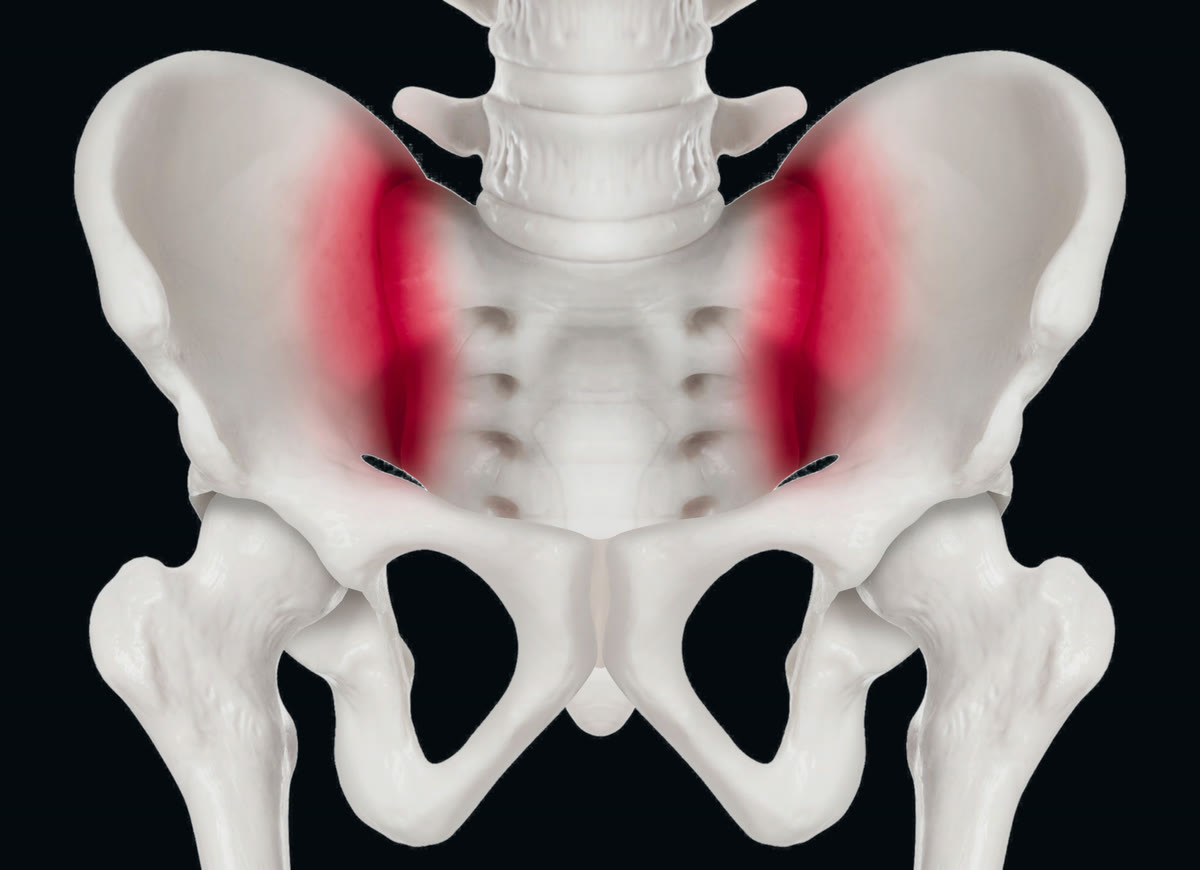

 Confirms Sacroiliac joint pain
Using X-ray guidance, we inject numbing medicine into the SI joint. If your pain goes away for a while, that confirms the joint is the source. Most insurers require this before a fusion. Additional details about SI joint injection, the diagnostic block
Sacroiliac joint pain
Through a small incision on the side of the hip, we place implants across the SI joint to hold it still so it can fuse. We only consider it after an injection has confirmed the joint is the source and other treatments have been tried. Additional details about MIS SI joint fusion
Sacroiliitis, or disruption after an injury
The joint between your spine and pelvis is causing pain low in your back and off to one side, sometimes spreading into your groin or thigh. It is often worse getting out of a car, rolling over in bed or standing on one leg. It is easy to mistake for a lumbar spine problem, and it is common after a lumbar fusion that ends at the sacrum.
First we examine the SI joint using a set of provocative maneuvers. If the physical exam is positive for sacroiliitis, then a diagnostic injection is the next step. If a numbing injection in your SI joint relieves your pain, this confirms that the SI joint is the source. If you fail multiple injections, then you may be a candidate for an SI joint fusion.
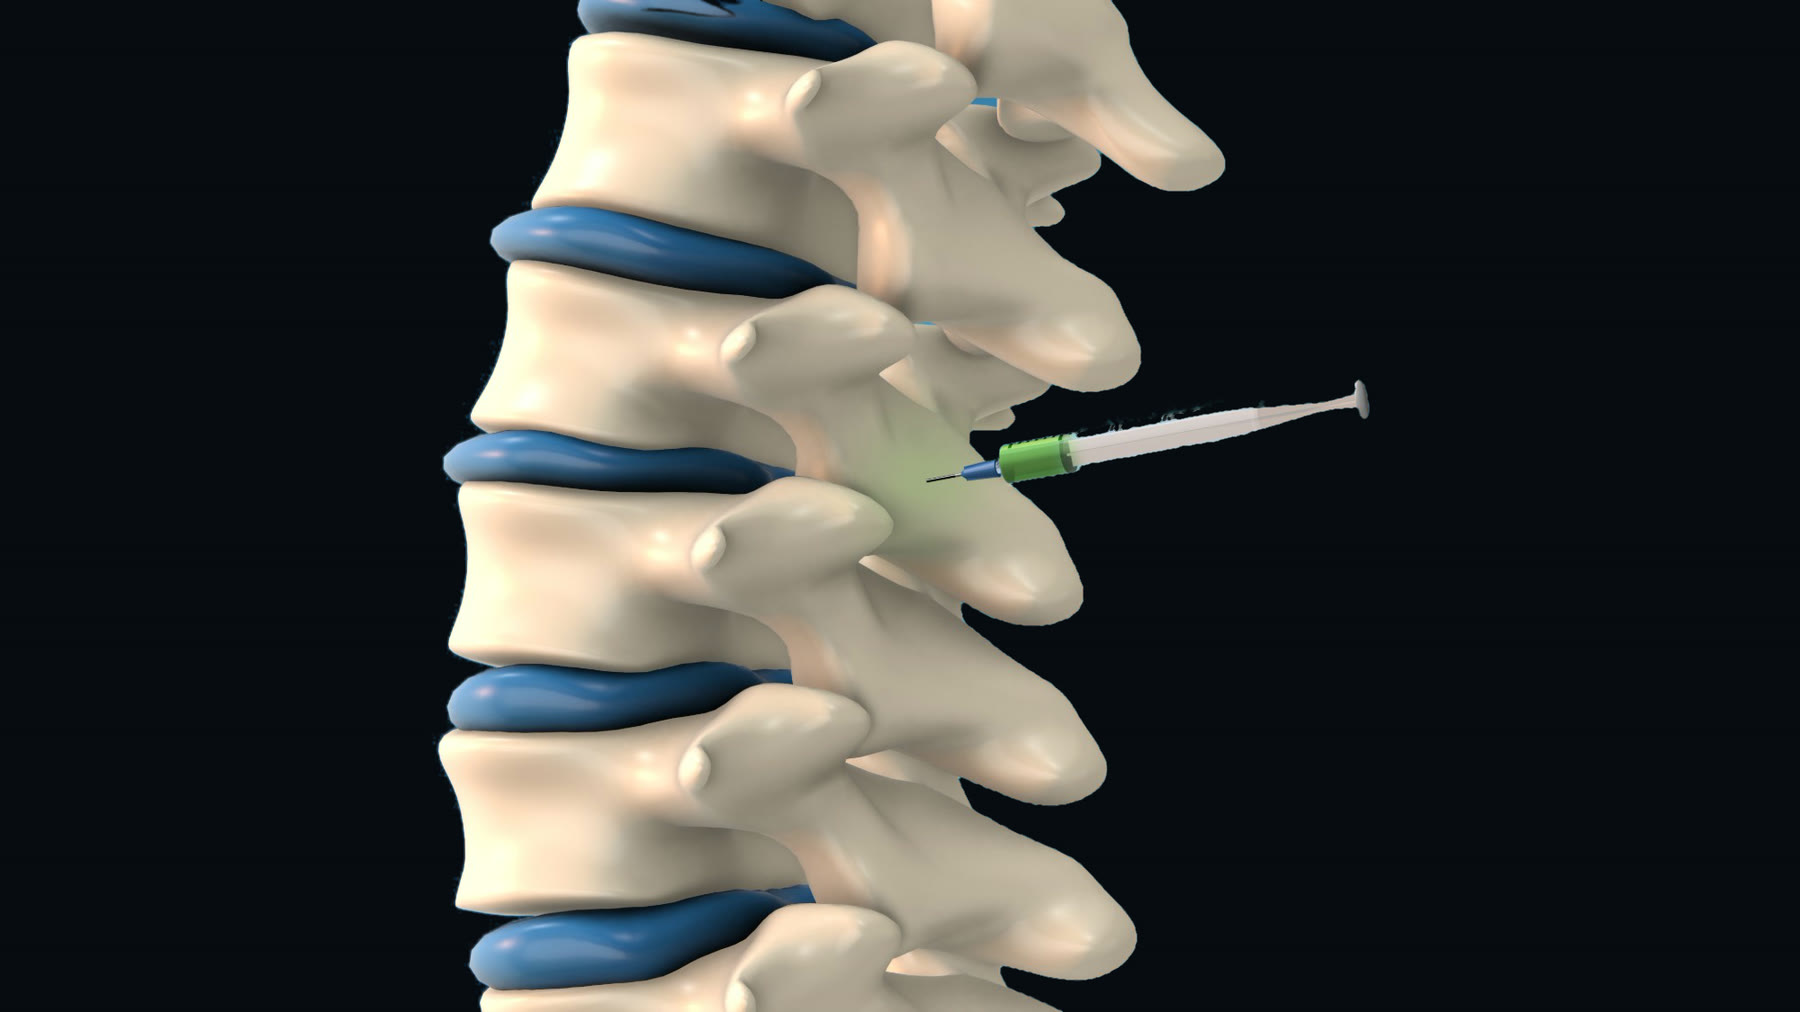 Pinched nerve
Spinal stenosis
Using X-ray guidance, we inject steroid medicine next to the irritated nerve to calm the inflammation. There is no incision. It can relieve the pain and helps confirm which level is causing it. Additional details about ESI, epidural steroid injection
 Degenerative back pain
Using X-ray guidance, we use heat to turn off the small nerves that carry pain from worn facet joints in the back. We first confirm those joints are the source with a numbing test injection. Additional details about RFA, radiofrequency ablation
Vertebrogenic back pain
Through a small needle in the back, we use heat to turn off the nerve inside the vertebra that carries this type of back pain. Nothing is removed or fused. Whether it is right for you depends on specific changes seen on your MRI. Additional details about BVN, basivertebral nerve ablation
An epidural steroid injection (ESI) involves injecting anti-inflammatory medicine (steroids) around a pinched or irritated nerve to help relieve leg pain. Radiofrequency ablation (RFA) helps relieve back pain by using heat to turn off small sensory nerves that innervate the spinal facet joints. Basivertebral nerve ablation (BVN), known as Intracept, targets the sensory nerves that travel to the vertebral endplates next to degenerative discs, which is another common cause of back pain. Intracept is a permanent solution that does not need to be repeated.
 Before
 After
 Before
 After
 Before
 After
Cervical disc replacement. X-rays and MRI before surgery, and after. About the operation →
 Before
 After
 Before
 After
 Before
 After
Posterior cervical fusion for cervical stenosis with myelopathy. MRI and X-rays before surgery, and after. About the operation →
 Before
 After
 Before
 After
 Before
 After
Lumbar fusion for spondylolisthesis. X-rays and MRI before surgery, and after. About the operation →
 Before
 After
 Before
 After
Microdiscectomy for a lumbar disc herniation. MRI before surgery, and after. About the operation →
From Dr. Zaidi’s own patients, shown with their written permission and with identifying details removed.